Veterinary Clinic Model
Healthcare Financial Model (Free Excel Download)
Forecast veterinary-clinic economics through appointments, procedures, average ticket, provider capacity, staffing, pharmacy sales, equipment capex, and location expansion.



professionals from Deloitte
Used by professionals from






About this model
Veterinary clinics depend on patient demand, the mix of services offered, and the capacity of veterinarians and technicians. This model helps you turn those operating drivers into a practical financial plan for a growing group of practices.
Use it to budget, assess a clinic acquisition, or plan expansion. It shows how changes in visit volume, pricing, staffing, boarding, and pharmacy sales affect profitability and value.
What every model includes
Live formulas, no hardcoded values
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
What's inside the Veterinary Clinic Model
- Clinic inputs: Year-1 clinics, new clinics per year, visits per clinic, veterinarians per clinic, average invoice
- Utilisation: Year-1 utilisation with an annual ramp and a practical ceiling
- Ancillary: boarding nights per clinic and average boarding spend, pharmacy spend per visit, price escalation
- Cost structure: veterinarian and support-staff comp and wage with benefits and wage growth, facilities, marketing, technology and SG&A as a percent of gross profit, depreciation, tax
- Capital and working capital: maintenance capex, clinic build-out cost per clinic, NWC, base-year revenue
- Valuation: WACC, terminal growth, net debt, shares outstanding
- Clinic roll-forward (opening + new = closing) with a utilisation ramp capped at a practical ceiling and closing clinics times visits per clinic giving total patient visits
- Medical revenue by tier (wellness-and-vaccines, sick-and-diagnostics, surgery-and-dentistry, emergency-and-specialty) with per-tier acuity indices, gross margins, and fee-schedule escalation
Veterinary Clinic Financial Model: How Operating Drivers Shape Valuation
This veterinary clinic financial model provides a structured seven-year operating forecast and unlevered DCF for a multi-location veterinary hospital group. It connects patient visit volumes, service mix, staffing, and capital expenditures to financial outcomes, helping users evaluate clinic growth, acquisitions, or expansion plans in a transparent, driver-based framework.
Operating Drivers: Clinics, Visits, and Capacity
The model builds volume from the clinic roll-forward: opening clinics plus new clinics equals closing clinics. Each clinic supports a mature number of patient visits, but actual visits depend on a utilisation ramp that starts at a first-year input and increases annually up to a practical ceiling.
- This reflects the real-world time needed for new or acquired hospitals to build their appointment book. Total patient visits—closing clinics multiplied by effective visits per clinic—drive veterinarian and technician headcount, making visit volume the most critical driver in the model.
- Growth is controlled by the annual number of new clinics, which also determines build-out capital expenditure.
Calculation Flow: From Service Mix to Gross Profit
Medical revenue is calculated tier by tier across wellness-and-vaccines, sick-and-diagnostics, surgery-and-dentistry, and emergency-and-specialty services. For each tier, patient visits are multiplied by the tier's share, the blended average invoice, and an acuity index that reflects the relative value of that service type.
- Higher-acuity tiers carry indices above one, while wellness visits sit below one, so the blended revenue per visit depends on the service mix. Boarding and grooming revenue is driven by closing clinics and boarding nights per clinic, while pharmacy and retail revenue depends on patient visits and spend per visit.
- All revenue lines are escalated at a fee-schedule step-up. Direct costs are then netted across all six revenue lines—the four medical tiers plus boarding/grooming and pharmacy/retail—using line-specific gross margins, yielding gross profit.
Cost Structure and EBITDA Build
Below gross profit, the model deducts veterinarian and technician/support labour, both of which are headcount-driven. Veterinarian compensation is acuity-weighted: the general-practice rate applies to the wellness and sick share of visits, while a specialty/ER premium multiplier applies to the surgery and emergency share.
- This aligns labour cost with the higher revenue these cases generate. A separate DVM recruiting and retention cost is calculated as veterinarian FTEs times turnover rate times cost per hire, capturing a sector-specific pressure.
- Overhead items—clinic facilities and equipment, marketing and client, technology, and corporate SG&A—are set as a percentage of gross profit, not revenue, because gross profit better reflects the scale of a high-margin practice. The result is EBITDA, followed by depreciation, EBIT, tax on positive EBIT, and net income.
Valuation and Practical Use
The model produces unlevered free cash flow by adding depreciation to NOPAT and subtracting maintenance capex, clinic build-out capex for new clinics, and the change in working capital. Working capital is a modest drag because veterinary services are largely paid at the point of service, leaving drug and pet-food inventory as the main tie-up.
- Free cash flows are discounted at the weighted average cost of capital, and a Gordon-growth terminal value is added to arrive at enterprise value. Net debt is then subtracted to get equity value and value per share.
- A dashboard summarises key metrics including clinics, patient visits, utilisation, revenue, EBITDA margin, enterprise value, and value per share. This structure supports budgeting, acquisition assessment, and expansion planning for a multi-location group.
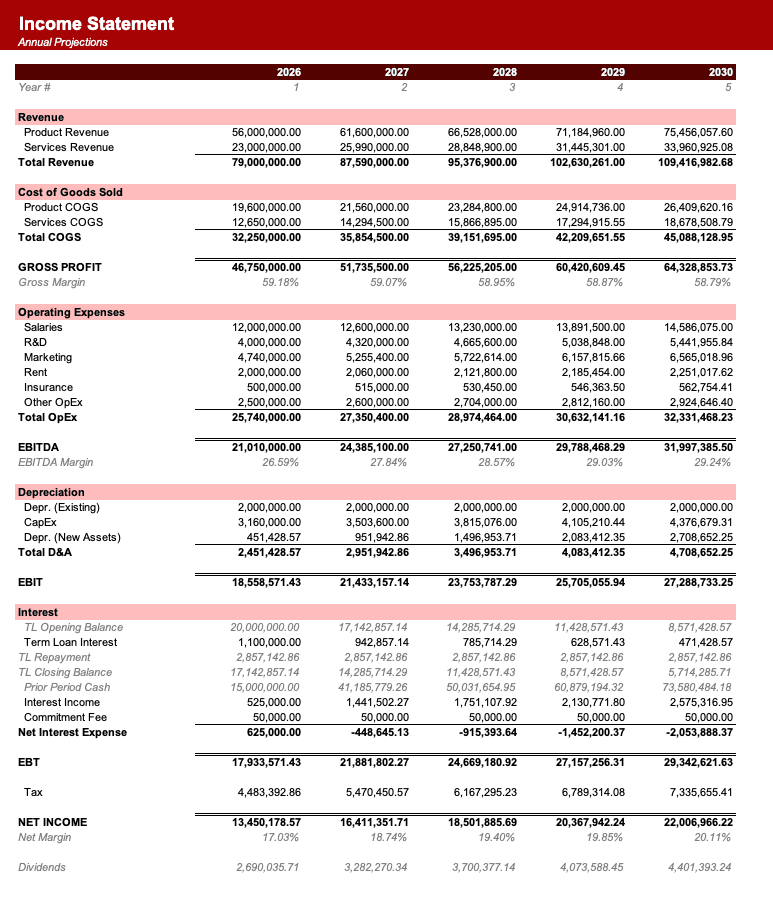
Formatted to IB standards
Named theme colors repaint the whole workbook in one click, on top of an investment-banking structure with clear input, output, and cross-sheet reference styling - brand-ready, institutional-grade, and fully auditable.

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Frequently asked
What is a veterinary clinic model?+
A veterinary clinic model captures the seven-year operating economics and intrinsic value of a multi-location veterinary hospital group that runs general-practice and specialty clinics alongside boarding, grooming and an in-house pharmacy. It rolls a clinic count forward, converts a capacity-utilisation ramp into total patient visits, prices visits across a four-tier service mix at a blended average invoice and acuity index, runs the labour-heavy cost stack to EBITDA, and discounts an unlevered free-cash-flow stream to enterprise value, equity value, and value per share.
How is veterinary revenue built?+
Total patient visits equal closing clinics times visits per clinic times a utilisation factor that ramps to a ceiling, and medical service revenue splits those visits across a wellness, sick-and-diagnostics, surgery-and-dentistry and emergency-and-specialty mix, each priced at a blended average invoice times a per-tier acuity index. Clinic-driven boarding and grooming and visit-driven pharmacy and retail layer on to total revenue.
Why is the service mix so important?+
An emergency or surgery case carries an acuity index well above one while a wellness or vaccine visit sits far below it, so the blended revenue per visit falls out of the mix. As the wellness tier share rises the blended figure compresses even with flat visit volume, which is why the model makes the per-tier indices and gross margins explicit so an analyst can flex the mix and watch revenue per visit, gross profit and EBITDA move together.
Why an unlevered DCF instead of an EBITDA multiple?+
A veterinary group still builds out each clinic and carries real depreciation and capex, so EBITDA overstates cash. The model bridges to unlevered free cash flow, NOPAT plus depreciation, less maintenance and build-out capex, less the change in working capital, which is light because care is paid at the point of service, and discounts it at a WACC, then adds a Gordon-growth terminal value. The implied EV/EBITDA falls out as a sanity check rather than as the valuation input.
How is total patient visit volume calculated?+
The Operations sheet multiplies closing clinics by effective visits per clinic. Effective visits per clinic is the mature visit capacity (set in Assumptions as visits per clinic) times the utilisation factor, which starts at the Y1 input and ramps by a fixed number of percentage points each year to a practical ceiling. A newly opened clinic typically takes two to four years to fill its appointment book, and the ramp captures that lag.
What is an acuity index and how does it affect revenue?+
The acuity index is a dimensionless multiplier applied to the average invoice for each service tier. Emergency and surgery cases carry indices above one; wellness and vaccine visits sit below one. Because per-tier revenue is patient visits times tier share times the average invoice times the acuity index, the blended revenue per visit falls directly out of the service mix. A shift toward wellness visits compresses blended revenue per visit even with flat total visit volume.
Why are overhead lines set as a percent of gross profit rather than revenue?+
Veterinary hospital groups run high blended gross margins (approximately 76% in this model) because the professional-service component is high-margin relative to medical supplies and lab cost. Overhead tied to gross profit rather than revenue avoids understating the cost of running multi-site hospitals, imaging suites, and a corporate platform, and makes EBITDA margin expansion a function of gross profit growth rather than top-line scale.
How is de novo clinic capex modelled in the DCF?+
The FCF sheet multiplies new clinics per year by a per-clinic build-out cost from Assumptions to derive de novo build-out capex. That figure is added to maintenance capex (set as a percent of revenue) and both are subtracted from NOPAT plus depreciation as real capital commitments, so the opening cadence reduces unlevered FCF and flows through the discounted valuation rather than sitting outside the model.
What are the headline outputs at the default inputs?+
At the default assumptions the model produces Y1 revenue of approximately $58.2M growing to approximately $138.9M by Y7 across 14 to 26 clinics and approximately 172,500 to 345,800 patient visits per year, a blended gross margin of approximately 76%, EBITDA margin ramping from approximately 19.2% to 21.6%, enterprise value of approximately $128.5M, value per share of approximately $10.50, and an implied EV/EBITDA of approximately 11.5x.
Have more financial modelling questions? Contact us
Related templates
Dental Practice
Five-year service-mix model: visits, production, collections, comp, and margins.
Pet Care Roll-Up Model
5-year veterinary-clinic roll-up: M&A pace, per-clinic economics, platform EBITDA, sponsor IRR and exit multiple arbitrage.
Hospital Operating Model
Operating model for hospital systems including inpatient/outpatient volumes, payer mix, DRG reimbursement, and staffing cost drivers.
Gym and Fitness Studio Operating Model
Operating model for fitness franchises and independent gyms including membership revenue, class scheduling, and facility utilization.