Medical Billing (RCM) Model
Healthcare Financial Model (Free Excel Download)
Forecast medical-billing operations through claims volume, collection rates, billing fees, payer mix, client retention, staff productivity, technology costs, and EBITDA.



professionals from Deloitte
Used by professionals from






About this model
This model helps an outsourced medical billing business plan its clients, claims, collections, and fee income. It shows how payer mix and denial rates affect what the business collects and the revenue it earns from healthcare providers.
Use it to test new-client growth, retention, collection performance, and staffing. The summary makes the effect on profit, cash flow, and value easy to see.
What every model includes
Live formulas, no hardcoded values
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
What's inside the Medical Billing (RCM) Model
- Client roster & claims inputs: opening clients, new clients signed, churn rate, claims per client, claims growth
- Billing & payer mix: average charge per claim, charge growth, commercial payer share and its annual decline
- Allowed amounts & denials: commercial/government allowed-amount ratios, commercial/government denial rates, appeal rate, appeal success rate
- Contingency fee schedule: commercial and government fee rates on cash collected
- Cost structure: claims per biller FTE, biller wage, clients per client-success FTE, client-success wage, corporate FTE and comp, benefits and wage growth, clearinghouse/EDI fee per claim, software & compliance cost per client, client-acquisition cost per new client, G&A and office overhead
- Tax: corporate tax rate on EBIT
- Capex & depreciation: technology capex per net-new FTE, platform development capex as % of revenue, useful life, base PP&E
- Working capital: commercial/government remittance lag, base fee receivable
Medical Billing Financial Model: How Payer Mix Drives Revenue and Cash Flow
This medical billing financial model projects seven years of operations for an outsourced revenue-cycle-management business. It shows how client growth, claims volume, payer mix, allowed amounts, denials, and contingency fees interact to shape cash collections and company revenue.
The model also covers staffing, per-claim costs, capital spending, working capital, and an unlevered DCF valuation. Rates and financial results described here reflect illustrative model settings, not industry benchmarks.
Client Roster, Claims Volume, and the Payer-Mix Schedule
The operations build begins with a client roll-forward: opening clients plus new signings minus churn equals closing clients. Claims processed then equal closing clients multiplied by claims per client, which grow at 2% annually.
- The defining feature is an explicit payer-mix schedule where the commercial share drifts downward each year—from 68.0% in Year 1 to 54.2% by Year 7—as the book diversifies toward government payers. This single visible row feeds the blended allowed-amount ratio, denial rate, remittance lag, and the split of collected cash between payer types.
- Because everything downstream traces back to one auditable schedule, the model's yield compression is transparent rather than buried in multiple independent assumptions.
Claims Funnel from Gross Charges to Collectible Cash
Gross charges billed are calculated as claims processed times average charge, with the charge per claim inflating 3% annually. That gross charge pool is multiplied by a mix-weighted allowed-amount ratio—64% commercial versus 26% government—to arrive at net collectible charges.
- A blended denial rate, mix-weighted at 5% commercial and 20% government, splits out denied dollars. Of those denied dollars, 70% are appealed, 45% of appeals succeed and recover at the same allowed ratio, and the remainder is written off and excluded from revenue.
- Clean claims plus recovered appeals sum to the total collectible pool, which is then split back into commercial and government cash using the same payer-mix schedule before applying contingency fees.
Revenue Build and Per-Claim Compression
Total revenue combines commercial cash collected at a 7.5% contingency fee and government cash collected at a 4.0% fee.
- Because the government share of the pool grows and carries a lower fee rate, the blended take rate on collections eases from 6.38% in Year 1 to 5.90% by Year 7—shown as its own KPI row.
- When the falling allowed ratio and rising denial rate are combined with this fee compression, revenue per claim processed declines from $20.05 to $19.59 even though average charge per claim inflates.
- Three separate compression levers just barely outrun one inflation driver, producing a realistic, narrow margin of decline rather than a smoothed result.
Cost Structure, Working Capital, and Valuation Outputs
Cost of goods sold is a per-claim clearinghouse fee of $0.28, a true unit cost rather than a margin assumption. Biller and client-success headcount scale with claims and clients respectively, while corporate headcount is fixed at five FTEs; all wages are loaded for benefits and escalated annually.
- Software, client-acquisition, G&A, and office overhead round out operating costs. Working capital is the fee receivable, tied to a payer-mix-weighted remittance lag that lengthens as government payers grow, making Year 1 free cash flow negative despite positive net income.
- The unlevered DCF discounts free cash flow at the stated WACC with Gordon-growth terminal value to produce enterprise value, equity value, and value per share, alongside dashboard KPIs such as EBITDA margin, revenue per claim, and blended fee percentage.
Formatted to IB standards
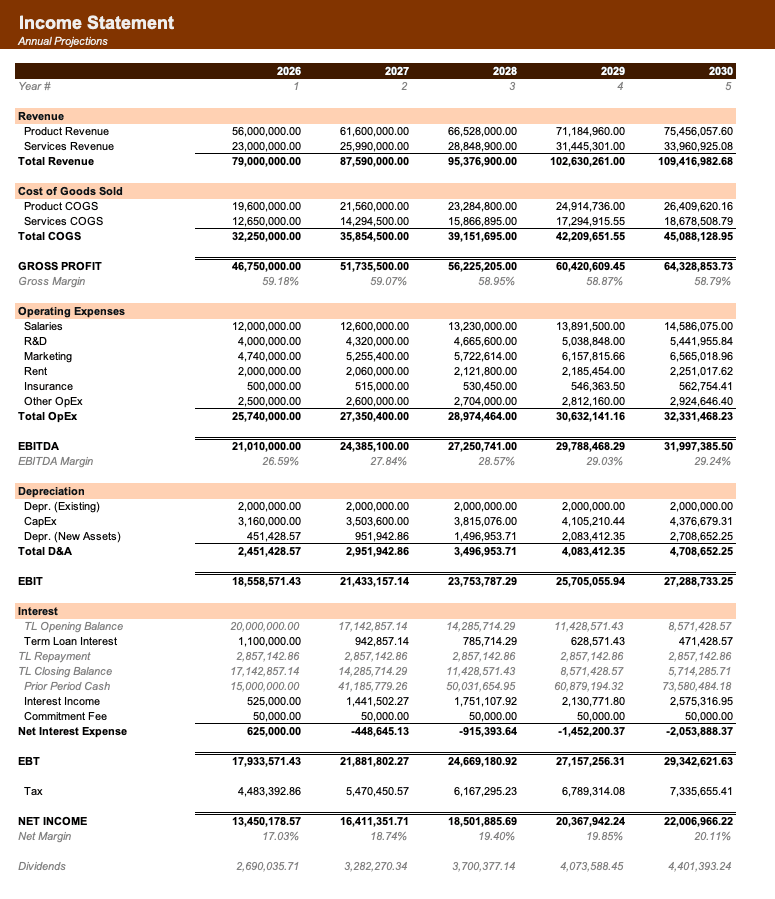
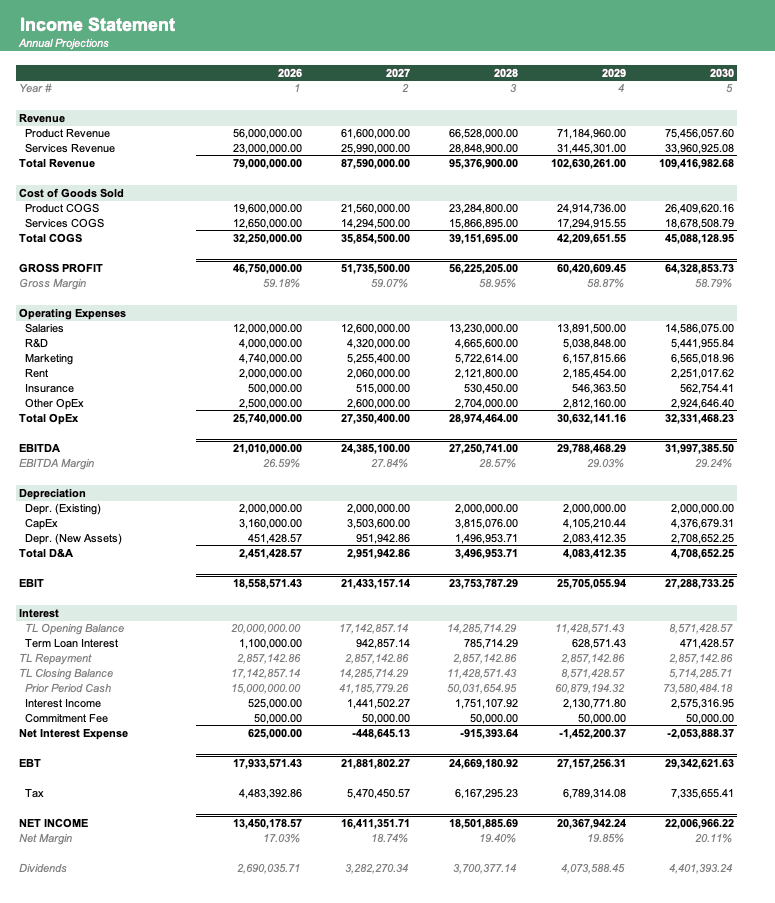
Named theme colors repaint the whole workbook in one click, on top of an investment-banking structure with clear input, output, and cross-sheet reference styling - brand-ready, institutional-grade, and fully auditable.

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Frequently asked
What is a medical billing (RCM) financial model?+
A medical billing financial model captures the seven-year operating economics and intrinsic value of an outsourced revenue-cycle-management company that processes claims on behalf of physician-practice clients. It rolls a client roster forward, converts the roster into claims processed and gross charges billed, and runs those charges through a payer-mix-weighted allowed-amount and denial funnel to arrive at cash actually collected. The billing company earns a contingency fee on that collected cash, split by payer type, and the model charges biller, client-success and corporate labour, a per-claim clearinghouse fee and revenue-geared overhead down to EBITDA, then discounts an unlevered free-cash-flow stream to enterprise value, equity value and value per share.
Why is revenue based on cash collected instead of gross billed charges?+
Because that is how RCM companies are actually paid. A billing company's contingency fee is a percentage of what it recovers for its client, not of what was originally billed, so the model has to build a real claims funnel: gross charges run through payer-specific allowed-amount ratios, a first-pass denial rate, an appeal recovery rate, and a write-off for claims that are never recovered, before the resulting collectible cash is priced at a contingency fee rate. Modelling revenue as a top-down growth rate would miss the economics entirely, since it is the funnel, not a percentage, that determines how much of every billed dollar actually turns into fee revenue.
Why does revenue per claim processed decline even though charges are inflating?+
Because the payer mix drifts from commercial-heavy toward government payers as the roster scales, and that one drift pulls three levers down at once: the blended allowed-amount ratio falls, since government payers reimburse far less of billed charges than commercial contracts; the blended denial rate rises, since government payers carry stricter documentation requirements; and the blended contingency fee rate falls, since government fee schedules are capped lower. All three compress together, so revenue per claim processed still falls from $20.05 to $19.59 across the horizon even against 3%-a-year charge inflation - the model shows the payer-mix cost of scaling into government-heavy claims, rather than smoothing it away.
Why is Year-1 free cash flow negative when the business is profitable?+
Because working capital in this model is the fee receivable - the contingency fee the billing company has earned but not yet been remitted - carried at a payer-mix-weighted remittance lag, not a percentage of revenue growth. As the government share of the payer mix grows, that remittance lag lengthens, so the receivable grows faster than the model's still-ramping EBITDA can fund out of NOPAT and depreciation alone. Year-1 unlevered free cash flow is consequently negative despite positive net income, turning solidly positive from Year 2 as EBITDA margin expands.
Have more financial modelling questions? Contact us
Related templates
Dental Practice
Five-year service-mix model: visits, production, collections, comp, and margins.
Outpatient Clinic Model
Plan and value a multi-specialty outpatient clinic group using provider capacity, visit volume, payer mix collections, and a DCF.
Urgent Care Model
Plan and value an urgent-care clinic group using visits, payer mix, staffing, and expansion assumptions.
Gym and Fitness Studio Operating Model
Operating model for fitness franchises and independent gyms including membership revenue, class scheduling, and facility utilization.