Outpatient Clinic Model
Operating Businesses Financial Model (Free Excel Download)
Model outpatient-clinic economics from visits, procedures, payer mix, reimbursement, provider capacity, staffing, supplies, facility costs, and operating cash flow.



professionals from Deloitte
Used by professionals from






About this model
This model helps you plan an outpatient clinic or a group of clinics across several medical specialties. It connects provider capacity, patient visits, payer mix, and collections to the staffing and operating costs of delivering care.
Use it to assess growth, a new clinic, or an acquisition. The summary shows how changes in productivity, reimbursement, and patient demand affect revenue, cash flow, and value.
What every model includes
Live formulas, no hardcoded values
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
What's inside the Outpatient Clinic Model
- Clinic & capacity inputs: Year-1 clinics, new clinics per year, providers per clinic, visits per provider-day, operating days
- Utilisation & no-show: Year-1 schedule fill with an annual ramp and a ceiling, no-show rate
- Specialty mix & charges: five specialty shares and expected charges per visit, ancillary per visit, fee escalation
- Payer mix & collections: commercial, public and cash-pay shares and per-payer collection rates
- Cost structure: provider comp; nurses per clinic and wage with benefits and wage growth; medical supplies per visit; rent per clinic; billing & collections and corporate G&A as % of revenue; depreciation; tax
- Capital & working capital: maintenance capex %, build-out cost per clinic, NWC % of revenue change, base-year revenue
- Valuation: WACC, terminal growth, net debt, shares outstanding
- Operations sheet: clinic roll-forward, provider headcount, schedule-fill ramp, visit capacity, scheduled and completed visits, nurse/tech headcount, visits per provider
How the Outpatient Clinic Financial Model Works
This outpatient clinic financial model provides a structured framework for evaluating a multi-specialty medical group. It connects provider capacity, patient visits, specialty charges, and payer collections to operating costs and cash flow.
The model is designed to support analysis of growth, new clinic openings, or acquisitions within the outpatient care sector.
Core Operating Drivers: Clinics, Providers, and Visit Volume
The model begins with a clinic roll-forward: opening clinics plus new clinics equals closing clinics. New clinics can represent de novo openings or tuck-in acquisitions.
- Closing clinics determine provider and nurse/tech headcount, as well as facilities costs. Provider headcount is calculated by multiplying closing clinics by providers per clinic.
- This provider base then drives visit capacity: providers times visits per provider-day times operating days. A schedule-fill factor, starting with a Year 1 input and ramping annually to a ceiling, converts capacity into scheduled visits.
Finally, scheduled visits are reduced by a no-show rate to arrive at completed visits. Visits per provider is the key productivity metric, reflecting the efficiency of the clinical workforce.
Revenue Build: Specialty Mix, Charges, and Collections
Completed visits are split across five specialty lines: primary care, dermatology, women's health, behavioral health, and diagnostics. Each specialty has a share and an expected charge per visit, which escalates annually.
- Multiplying visits by specialty share and charge yields gross patient charges by specialty. These charges are not equivalent to cash.
- A blended collection rate, based on payer mix (commercial, public, and cash-pay shares) and each payer's collection efficiency, converts gross charges into net patient service revenue. Ancillary income from labs, imaging, and in-house pharmacy dispensing is added on a per-visit basis.
This revenue build, including the collection rate, reflects the complex reimbursement environment of outpatient care.
Cost Structure and Profitability
The P&L starts with total revenue and subtracts operating costs. Provider compensation and nurse/tech staff are headcount-driven, including benefits and annual wage growth.
- Medical supplies are charged per completed visit. Facilities and rent are charged per clinic.
- Two distinct overhead lines are modeled: billing & collections (revenue-cycle management) as a percentage of net patient revenue, and corporate G&A as a percentage of total revenue. These costs yield EBITDA, then depreciation, EBIT, tax, and net income.
Because revenue grows with schedule-fill ramp and fee escalation while per-clinic and per-visit costs grow with headcount, volume, and inflation, the model typically shows EBITDA margin expansion over the forecast horizon.
Cash Flow and Valuation within the Outpatient Clinic Financial Model
Unlevered free cash flow is derived from NOPAT, adding back depreciation, subtracting maintenance capex and clinic build-out capex, and adjusting for changes in working capital. Working capital is a real cash drag because insurance receivables run 30-50 days, tying up a portion of revenue growth.
- The DCF valuation discounts explicit free cash flows at the WACC and adds a Gordon-growth terminal value to arrive at enterprise value. Subtracting net debt yields equity value and value per share.
- The model also reports implied EV/EBITDA. A dashboard summarizes key metrics including clinics, completed visits, revenue, EBITDA margin, and enterprise value, enabling users to assess the financial impact of operating and reimbursement assumptions.
Formatted to IB standards
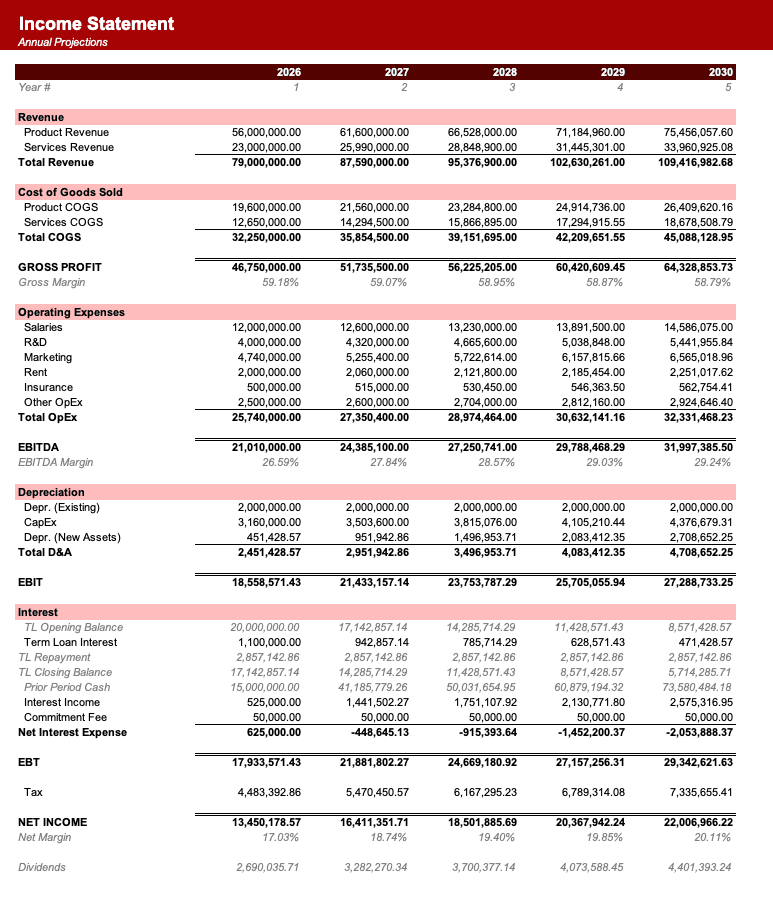
Named theme colors repaint the whole workbook in one click, on top of an investment-banking structure with clear input, output, and cross-sheet reference styling - brand-ready, institutional-grade, and fully auditable.

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Frequently asked
What is an outpatient clinic financial model?+
An outpatient clinic financial model captures the seven-year operating economics and intrinsic value of a multi-specialty outpatient medical clinic group - the physician-practice-management platform that sponsors and health systems roll up out of independent practices. It rolls a clinic count forward, builds provider-driven visit capacity net of no-shows, prices a five-specialty charge mix, converts charges to cash through a payer-mix collection rate, charges revenue-cycle management as its own line, and discounts an unlevered free-cash-flow stream to enterprise value, equity value and value per share.
Why is capacity provider-driven rather than clinic-day-driven?+
Throughput in a multi-specialty group is set by clinicians: closing clinics times providers per clinic gives provider headcount, and providers times visits-per-provider-day times operating days gives annual capacity, which a schedule-fill ramp fills net of a no-show rate. This makes provider recruitment, slot utilisation and the no-show rate the operating dials, with visits per provider as the headline productivity metric - the right shape for a people-intensive practice group.
Why are charges different from collected cash?+
Gross charges are built specialty by specialty at specialty-specific expected charges, but only a fraction is collected. Net patient revenue is gross charges times a blended collection rate - the sum over payers of each payer's share times its collection efficiency, net of contractual adjustments, denials and bad debt. Commercial and public payers collect near par while self-pay collects well below it, so the payer mix moves realised revenue independent of volume or price, and revenue-cycle management is charged as its own cost line.
Why an unlevered DCF, and what about working capital?+
The bridge charges maintenance and clinic build-out capex and a real working-capital call - third-party payer receivables run a month or more, so a fraction of revenue growth ties up in working capital - then discounts unlevered free cash flow at a WACC reflecting the recurring, demographically supported character of outpatient demand tempered by reimbursement and clinician-supply pressure. Enterprise value bridges through net debt to value per share, with the implied EV/EBITDA as a sanity check.
Have more financial modelling questions? Contact us
Related templates
Urgent Care Model
Plan and value an urgent-care clinic group using visits, payer mix, staffing, and expansion assumptions.
Physical Therapy Clinic Model
Plan and value an outpatient physical therapy clinic group using patient visits, payer reimbursement rates, staffing, and a DCF.
Veterinary Clinic Model
Plan and value a veterinary clinic group using patient visits, services, staffing, and expansion assumptions.
Food Manufacturing Model
Operating model for food production and processing businesses with ingredient sourcing, production scheduling, and margin analysis.