Hospice Care Provider Model
Healthcare Financial Model (Free Excel Download)
Forecast hospice-provider economics from census, admissions, length of stay, reimbursement, visit intensity, clinical staffing, compliance costs, and branch expansion.



professionals from Deloitte
Used by professionals from






About this model
This model helps you plan a hospice provider supporting patients and families through end-of-life care. It connects referrals, patient census, length of stay, and care needs to the nurses, clinicians, facilities, and support services required to deliver compassionate care.
Use it to assess an acquisition, new market, or growth plan. Test referral demand, staffing, reimbursement, and care mix to understand the effect on finances and business value.
What every model includes
Live formulas, no hardcoded values
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
What's inside the Hospice Care Provider Model
- Admissions & census inputs: Year-1 admissions, admission growth rate, average length of stay (ALOS) and its annual increase
- RHC two-tier per diem: Tier 1 and Tier 2 rates, the day-61 tier threshold, and the hospice payment rate update
- Other levels of care: CHC, IRC and GIP per-diem rates and day shares
- Payer mix & the Medicare hospice aggregate cap: Medicare mix %, cap amount per beneficiary and its annual update
- Interdisciplinary team staffing: five role ratios (RN, aide, social worker, chaplain, volunteer coordinator) and wages, benefits load, wage growth
- Medical director, physician & bereavement: fixed medical director fee, physician visits per ADC and fee per visit, CMS-required bereavement cost per admission
- Drugs, DME & supplies: cost per patient-day
- Overhead staffing & capex: back-office ratio and wage, QA and corporate FTE and wages, field-device capex per net-new FTE, EMR platform capex %, useful life, base PP&E and clinical FTE
Inside a Hospice Financial Model: Cap, Staffing, and Valuation
This hospice financial model projects a Medicare-certified provider over seven years, linking referrals to patient days, per-diem revenue, staffing, and valuation. It makes the Medicare aggregate cap a visible constraint and derives care costs from census.
The page explains the model's documented drivers, calculation flow, outputs, and practical use for evaluating acquisitions or growth plans.
Admissions, Length of Stay, and Level-of-Care Mix
The model begins with annual referral admissions, which grow from a base year at a set rate, and an average length of stay (ALOS) that rises linearly. Patient days equal admissions times ALOS, and average daily census (ADC) is patient days divided by 365.
- Those days are split across four levels of care—routine home care (RHC), continuous home care (CHC), inpatient respite care (IRC), and general inpatient care (GIP)—with RHC representing the vast majority. Each level carries its own per-diem rate, and the RHC rate is further divided into two tiers: a higher rate for days 1–60 and a lower rate for day 61 onward.
- The Tier 2 share is derived directly from ALOS, so as ALOS rises, a larger portion of RHC days prices at the lower tier. This mechanically ties the length-of-stay assumption to the blended per-diem rate, creating a natural compression in revenue per day even as individual rates inflate.
CHC, IRC, and GIP are held at small, flat day shares but carry materially higher per-diem rates, adding a premium to the overall blended rate.
The Medicare Aggregate Cap and Net Revenue
A defining feature of this hospice financial model is the Medicare aggregate cap, a regulatory clawback that limits total Medicare payments per beneficiary. The model calculates an aggregate cap dollar amount by multiplying a cap per beneficiary (inflated annually) by the number of beneficiaries served, approximated as Medicare mix percentage times admissions.
- Medicare revenue gross is then tested against this cap each year, and any excess is recorded as a contra-revenue overage that reduces net patient revenue. The overage is zero in early years when revenue per beneficiary is below the cap, but as ALOS lengthens, average revenue per beneficiary climbs.
- Eventually, it exceeds the inflating cap, triggering an overage that grows in later years. This mechanic directly links case-mix to profitability and highlights a genuine regulatory constraint.
Non-Medicare revenue is added to net Medicare revenue to arrive at total net patient revenue, which feeds the P&L and valuation.
Bottom-Up Staffing and Cost of Care
Instead of using a percentage of revenue, the model builds the interdisciplinary team (IDT) from average daily census. Five roles—RN case managers, hospice aides, social workers, chaplains, and a volunteer coordinator—scale at specific caseload ratios per ADC.
- Each role carries a wage that escalates annually and a benefits load. Layered on top are a fixed medical director fee, per-visit physician fees, and a CMS-required bereavement program cost per admission.
- Drugs, durable medical equipment, and medical supplies are modeled as a cost per patient day because they are not separately billable under the Medicare Hospice Benefit. Together, IDT labor, medical and bereavement costs, and supplies form the cost of hospice care.
This bottom-up approach ensures costs grow with patient volume and reflect the true unit economics of delivering hospice services, rather than relying on a margin assumption.
Outputs, Valuation, and Practical Use
The model flows through to a P&L, unlevered free cash flow, and a discounted cash flow valuation. It outputs key metrics on a dashboard, including admissions, ALOS, cap overage, revenue, EBITDA margin, net income, enterprise value, and value per share.
- The P&L starts with net patient revenue, subtracts the bottom-up cost of hospice care, then overhead, marketing, G&A, and insurance to reach EBITDA. Depreciation and taxes lead to net income.
- Free cash flow is NOPAT plus depreciation minus capex and changes in working capital, where working capital is the Medicare claims receivable based on a billing lag. The DCF discounts free cash flow at WACC and adds a Gordon-growth terminal value to derive enterprise value, then adjusts for net debt to get equity value.
This structure allows users to test referral demand, staffing, reimbursement, and care mix, and to assess acquisitions, new markets, or growth plans by seeing how regulatory and operational drivers affect financial outcomes and business value.
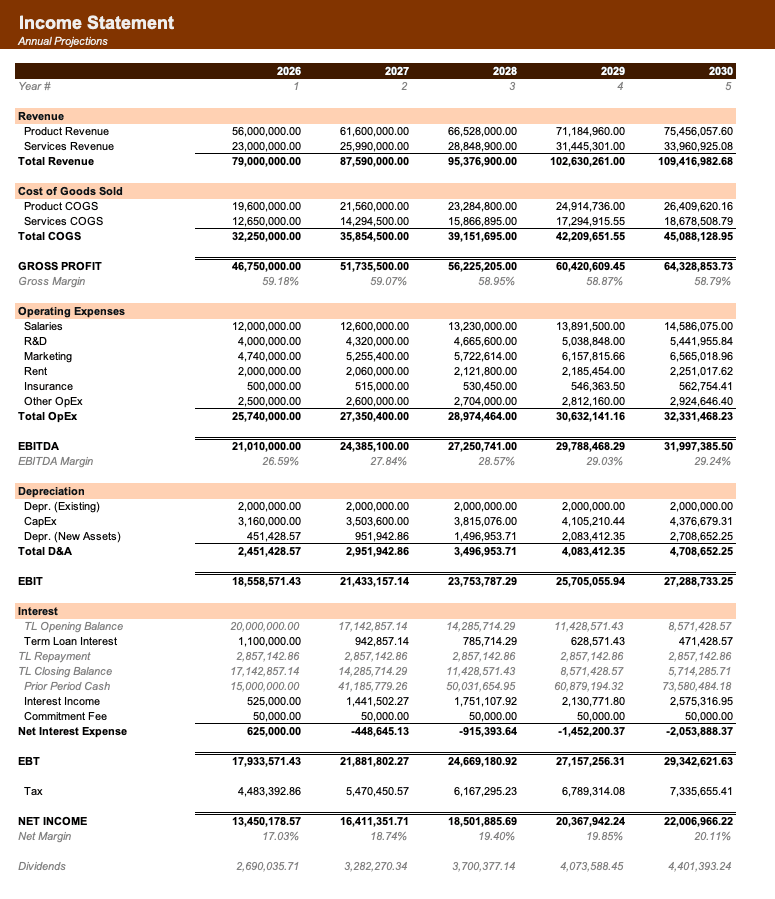
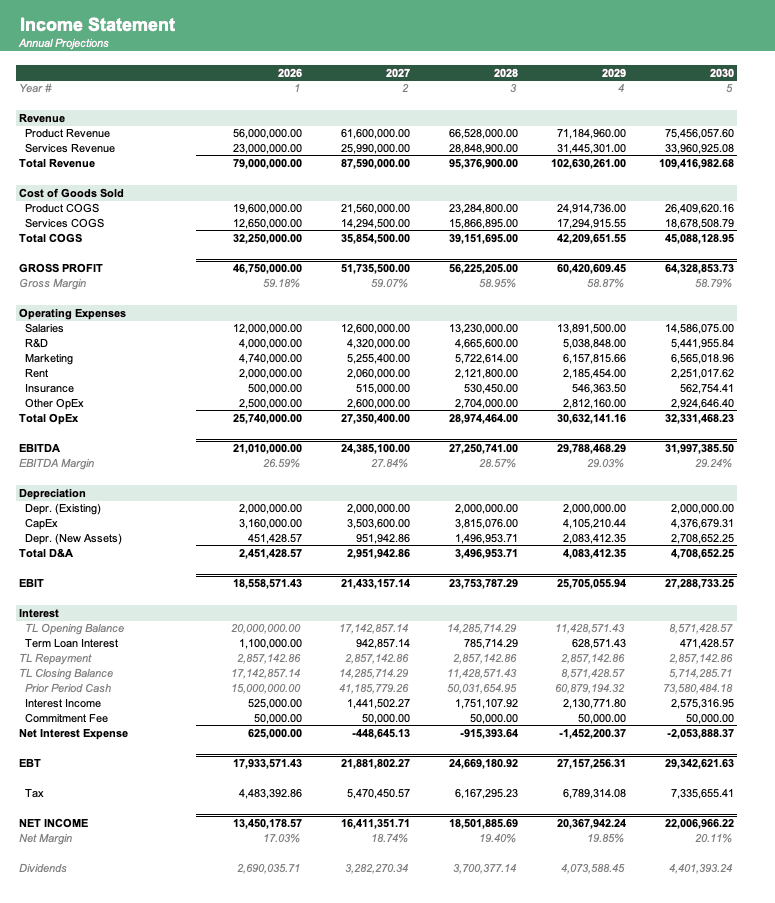
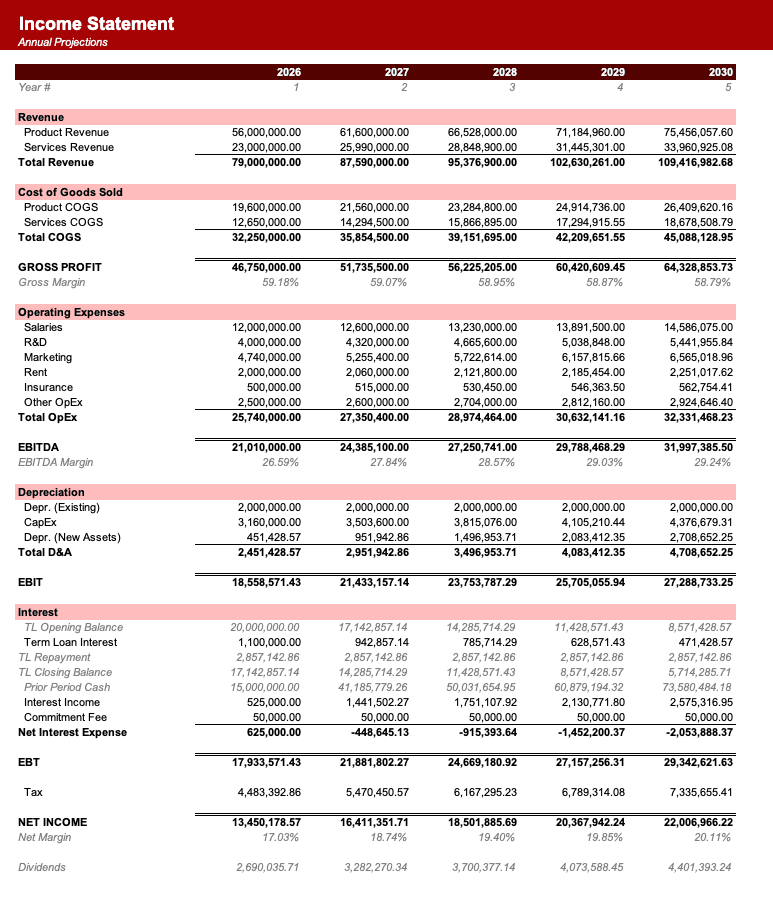
Formatted to IB standards
Named theme colors repaint the whole workbook in one click, on top of an investment-banking structure with clear input, output, and cross-sheet reference styling - brand-ready, institutional-grade, and fully auditable.

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Frequently asked
What is a hospice financial model?+
A hospice financial model captures the seven-year operating economics and intrinsic value of a Medicare-certified hospice - routine home care, continuous home care, inpatient respite care and general inpatient care delivered to terminally ill patients electing the Medicare Hospice Benefit. It rolls referral admissions and average length of stay into patient days, prices those days by level of care including a two-tier routine-home-care per diem, tests Medicare revenue against the Medicare Hospice Aggregate Cap, derives the interdisciplinary care team bottom-up from Average Daily Census, and discounts an unlevered free-cash-flow stream to enterprise value, equity value and value per share.
What is the Medicare hospice aggregate cap and why does it matter?+
The Medicare Hospice Aggregate Cap is an annual, per-beneficiary regulatory limit: CMS compares a hospice's total Medicare payments in a cap year against a statutory cap-per-beneficiary amount multiplied by the number of Medicare beneficiaries it served, and if payments exceed that amount, the hospice must repay the excess. It matters because it is a real, audited clawback - not a modeling abstraction - that disproportionately affects hospices whose average length of stay runs long, since payment per beneficiary rises with days of care while the cap amount does not adjust for case mix.
Why does the Tier 2 share of routine home care days climb from 20% to 64%?+
Because it is mechanically derived from average length of stay (MAX(0, (ALOS-60)/ALOS)), not set as an independent trend. As the hospice's admission growth shifts from short, hospital-referred cancer admissions toward long, SNF- and dementia-referred stays, average length of stay rises from 75 to 165 days, and a mechanically larger share of each patient's routine-home-care days fall past the day-60 tier threshold - the same case-mix shift that separately pushes average Medicare revenue per beneficiary past the aggregate cap.
Why does EBITDA margin expand and then reverse instead of moving in one direction?+
Because two different forces dominate at different points in the horizon. Through Year 4, a fixed overhead base (compliance/QA and corporate FTE held flat) deleverages faster than interdisciplinary staffing and per-day supply costs scale, so EBITDA margin actually expands from 19.9% to 21.3%. From Year 5, the aggregate cap overage begins cutting directly into net revenue while patient volume and cost keep growing, reversing that expansion to 8.8% by Year 7 - an honest result showing the regulatory clawback outweighing operating leverage once the case mix has shifted far enough toward long-stay referrals.
Have more financial modelling questions? Contact us
Related templates
Home Health Agency Model
Plan and value a Medicare home health agency using episode admissions, PDGM case-mix payments, clinical visits, and a DCF.
Medical Billing (RCM) Model
Plan and value a medical billing (RCM) company using claims volume, collection rates, contingency fees, and a DCF.
Outpatient Clinic Model
Plan and value a multi-specialty outpatient clinic group using provider capacity, visit volume, payer mix collections, and a DCF.
Gym and Fitness Studio Operating Model
Operating model for fitness franchises and independent gyms including membership revenue, class scheduling, and facility utilization.