Emocha Financial Model
Health-tech Startup Financials (Free Excel Download)
Digital Medication Adherence Program using video-based directly observed therapy (DOT) and a clinical adherence team to confirm dose-by-dose ingestion for transplant patients and other chronic condition populations.



professionals from Deloitte
Used by professionals from






About this model
emocha provides a digital medication-adherence programme using video-based directly observed therapy and a clinical adherence team. It helps transplant and chronic-condition patients confirm dose-by-dose medication use for health systems and care providers.
The product is sold as a bundled institutional programme rather than a standalone consumer app. Its likely commercial structure is a per-patient-per-month fee that combines software, analytics, and human clinical support.
The model should forecast transplant-centre customers, enrolled patients per centre, PPPM pricing, enrolment duration, and renewal. Clinical staffing, technology, onboarding, and outcomes-related economics should be separately modelled against recurring programme revenue.
A turnkey financial model
Live formulas, no hardcoded values
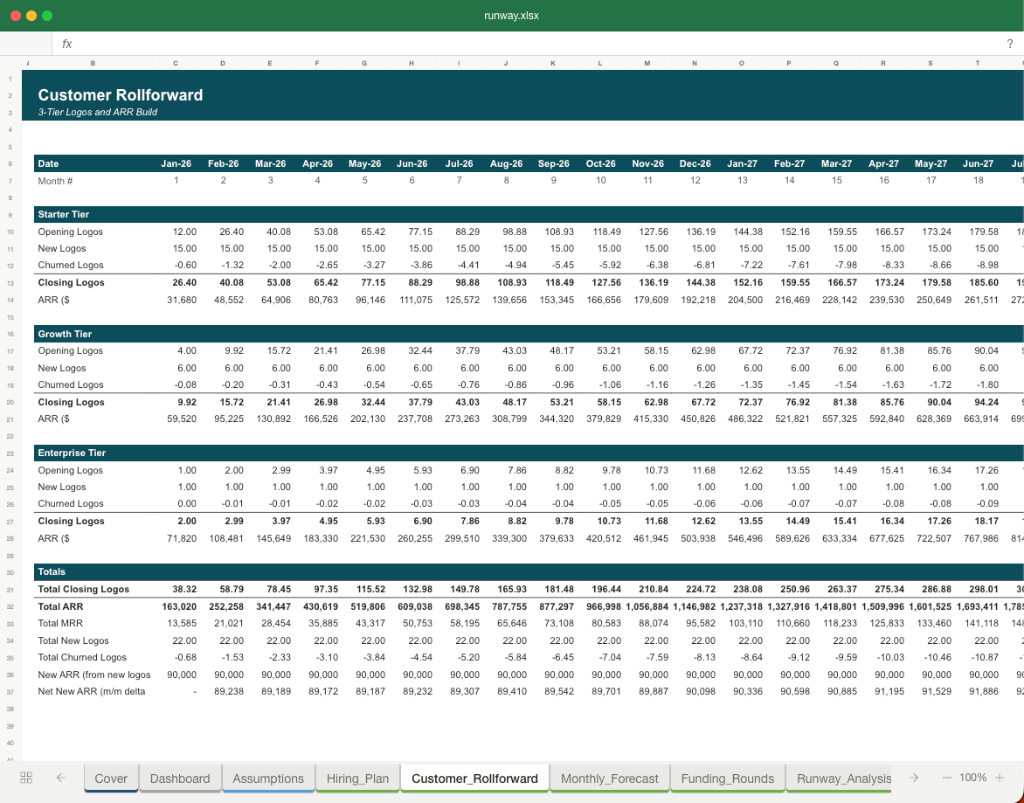
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
About Emocha
emocha.com
How to build a detailed financial model for Emocha
A complete walkthrough of the business, drivers, and assumptions behind the downloadable Emocha model - distilled from its pitch deck and publicly available information.
Product & value proposition
- Core product: emocha mobile app + clinical adherence team + analytics/reporting platform for transplant teams.
- Patient side: Daily video selfie of medication ingestion, side effect reporting, in-app messaging with adherence coach, asynchronous and live video, reminders, 22 languages.
- Clinical team side: Pharmacists do medication reconciliation at program outset; adherence coaches review all videos and provide daily support; registered nurses review symptoms and liaise with care teams.
- Transplant team side: Weekly/monthly analytics reports, access to video check-ins, escalation alerts.
- Mechanism: CDC-endorsed directly observed therapy (DOT) applied digitally - measures ingestion, not just possession.
- Program structure: 3-month daily DOT → ongoing support & medication management.
Market
- Problem scale (transplant): Non-adherence ranges 20–70% across kidney, heart, and liver transplant patients.
- 40% of rejections linked to medication non-adherence.
- 2/3 of non-adherent patients experience graft failure.
- Hospitalization costs from rejection episodes: $4K–$11K.
- Non-adherent patients have 7x greater risk for late rejection.
- Adjacent indications addressed: TB, Hepatitis C, Asthma, Type 2 Diabetes (per clinical evidence slides).
- Existing traction: Standard of care for 450 health departments - likely from prior TB/public-health DOT use, predating the transplant pivot.
Revenue model
- Inferred model: B2B subscription or per-patient-per-month (PPPM) fee charged to transplant centers / health systems. Standard for digital health managed care services.
- Service bundling: Platform (app + analytics) + managed clinical team (pharmacists, coaches, nurses) appear to be sold together as a program - not unbundled.
- Channel: Direct sales to transplant programs at academic medical centers and health systems (named partners: Johns Hopkins, FSU, UF, UVA, U Miami).
- Government funding channel: NIH SBIR grant (R44DK123978) - non-dilutive revenue/grant income.
Traction & metrics
- 450 health departments served (standard of care)
- 50-person team
- 15+ peer-reviewed studies validating the platform
- Active transplant program metrics (pilot cohort, slide 17):
- 75 total enrolled patients
- 92% average adherence rate for active patients
- 6.8% patients required escalation
- 8,456 total observed video check-ins
- 915 total hours of observed check-ins
- 2,893 check-ins in past month / 257 hours
- 125 escalations to nurse/pharmacist
- 27 escalations to transplant team
- 243 adherence challenges logged
- Patient adherence breakdown: 60% at 81–100%, 30% at 61–80%, 2% at 41–60%, 5% at 21–40%, 3% at 0–20%
Unit economics
- TB DOT program: $8K saved per patient - cost-avoidance data point, not revenue/margin.
Competition / moat
- Differentiation stated: Only comprehensive Digital MAP combining video technology + human engagement + CDC-endorsed DOT methodology.
- Evidence moat: 15+ peer-reviewed studies (NIH, CDC, Johns Hopkins partnerships).
- Clinical proof points across 5 conditions: TB (92–95% adherence, $8K saved/patient), TB-CDC (87–92% adherence, 100% treatment completion), Hepatitis C (98% adherence in drug-using population), Asthma (92% adoption, 73% reduction in ED visits*), Type 2 Diabetes (86% adherence, 50% reduction ED visits, 27% reduction hospital admissions*). *Pending publication.
- Existing competitors: Not named in deck.
- Network/switching moat: Integration with transplant team workflows; playbook specificity to transplant; branded clinical team.
Team & funding ask / use of funds
- Team: 50-person multidisciplinary team - nurses, pharmacists, public health technologists.
- Origin: Johns Hopkins spin-out, Baltimore-based.
- Founding/leadership team: Not individually named in deck.
- NIH SBIR grant: Award R44DK123978 (National Institute of Diabetes and Digestive and Kidney Diseases).
- Institutional partners: Johns Hopkins University, Florida State University, University of Florida, University of Virginia, University of Miami, NIDDK.
Recommended financial model
- Archetype + why: B2B Digital Health SaaS / Managed Care Services - per-patient-per-month (PPPM) revenue model. The business sells a bundled program (app + clinical team + analytics) to transplant centers under an institutional contract. Revenue is best modeled as: (# transplant center clients) × (avg enrolled patients per center) × (PPPM fee). The clinical team is a meaningful COGS driver (labor-intensive: coaches, nurses, pharmacists), making gross margin and headcount modeling critical. This is not a pure SaaS play - the human services layer makes it closer to a tech-enabled services business with ~40–60% gross margins.
- Forecast horizon & granularity: 5-year annual model (Year 1–5), with Year 1 monthly for cash/headcount planning. Given NIH grant dependency and early commercial stage, monthly burn visibility in Year 1 is important.
- Key drivers & assumptions:
| Driver | Value | Source |
|---|---|---|
| Active transplant center clients (Y1) | 5 | handful of named partners, early commercial |
| Active transplant center clients (Y5) | 50–100 | ~900 transplant programs in US |
| Avg enrolled patients per center | 75 | - |
| Patient ramp per center (months to fill) | 6–12 | - |
| Program duration per patient (months) | 3–6 (DOT phase) + ongoing | - |
| PPPM fee | $150–$300 | digital health managed care services range; not in deck |
| Clinical team labor (COGS % of revenue) | 45–55% | high-touch model with nurses/coaches/pharmacists |
| Platform/tech COGS | 5–10% | - |
| Gross margin | 35–50% | - |
| Operating team (current) | 50 FTEs | - |
| NIH grant revenue (non-dilutive) | Not quantified | - |
| Patient adherence rate (clinical outcome) | 92% | - |
| Escalation rate (nurse/pharmacist) | 6.8% | - |
| Churn (center-level annual) | 10–15% | - |
| NRR | 90–110% | expansion via more patients per center |
| $8K cost savings per TB patient | use as ROI proof for sales/pricing model |
- Scenarios (Base / Bull / Bear - which variables flex):
- Bear: Slow enterprise sales cycles; only 3 new centers/year; low PPPM ($150); gross margin pressure from labor costs; NIH grant not renewed.
- Base: 8–10 new centers/year; PPPM ~$200; gross margin 40–45%; NIH grant continues through R44 period.
- Bull: Payer reimbursement unlocked (Medicaid/CMS coverage for DOT); PPPM ~$275+; expansion to non-transplant indications (asthma, diabetes per slide 12); 20+ new centers/year.
- Required sheets / outputs:
- Assumptions - PPPM, patient volumes, center ramp, headcount ratios, grant income
- Revenue build - centers × patients × PPPM; grant revenue line
- P&L - Revenue, COGS (clinical labor, platform), gross profit, OpEx (S&M, R&D, G&A), EBITDA
- Headcount model - clinical team scales with patients; sales/admin scales with centers
- Cash flow / runway - monthly burn in Year 1; NIH grant receipts; fundraise timing
- Unit economics summary - LTV/CAC by cohort; payback period; gross margin per patient
- Sensitivity table - PPPM vs. patients per center; gross margin vs. labor cost rate
Frequently asked
Is the Emocha financial model free?+
Yes. The Emocha model is a free Excel (.xlsx) download with live formulas. Sign up with your email and the workbook is yours to keep, review, and edit.
What's included in the model?+
A 5-year monthly forecast with P&L, cash flow and runway, valuation (exit multiple plus a DCF cross-check), MOIC/IRR returns, and unit economics, with live formulas throughout.
How was this model built?+
It was built from Emocha's pitch deck and publicly available information, then structured to investment-banking standards as a fully editable Excel model.
Can I change the assumptions?+
Yes. You can change assumptions and the live formulas will recalculate in the downloadable Excel model.
Have more financial modelling questions? Contact us

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Other Health-tech Startup Financial Models
Browse another startup in the same category.
98point6
B2B SaaS platform licensing an AI-powered virtual care technology stack to health systems, pivoted from running a direct-to-employer virtual clinic.
A-Champs
IoT-powered gamified training device (ROXs PRO) for sports/health professionals, evolving into a B2C smart coach app for families.

AccuRx
Patient-centred communication platform connecting everyone involved in a patient's care, starting with near-universal penetration in UK GP practices.

Aeris
Swiss-made premium air purifiers sold through DTC, retail, and dealer channels, with a recurring filter consumable attached to a connected mobile app.

Akido Labs
Akido Labs is a data-driven prevention platform that integrates siloed healthcare, municipal, and non-profit data to enable proactive outreach and case management for vulnerable populations (homeless, chronically ill, etc.).

Alloy
Telehealth + DTC subscription platform delivering menopause hormonal treatment (MHT) and holistic care to U.S. women 40+.

Astek Diagnostics
Point-of-care diagnostic device (Jiddu system) that confirms bacterial infections and antibiotic sensitivity in ~1 hour across four body fluid types (urine, CSF, effluent, blood).

Atom Limbs
Atom Limbs is building the first AI-powered, neural-controlled prosthetic arm sold direct-to-consumer on a subscription model.