Everside Health Financial Model
Health-tech Startup Financials (Free Excel Download)
Technology-enabled primary care platform that partners with self-funded employer plan sponsors to deliver lower-cost, higher-quality healthcare for their employees.



professionals from Deloitte
Used by professionals from






About this model
Everside Health is a technology-enabled primary-care platform partnering with self-funded employers to provide lower-cost, higher-quality care for employees. It operates onsite, nearsite, and virtual delivery models rather than simply licensing software.
Employer plan sponsors sign recurring multi-year contracts, typically structured per employee per month or around dedicated health centres. The company had a substantial direct B2B client base, making contract retention and care utilisation central.
The model should forecast employer clients, eligible employees, PEPM revenue, health-centre openings, utilisation, and renewals. Provider staffing, facility costs, virtual-care delivery, market launch cost, and client concentration should be included in the services forecast.
A turnkey financial model
Live formulas, no hardcoded values
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
About Everside Health
eversidehealth.com
How to build a detailed financial model for Everside Health
A complete walkthrough of the business, drivers, and assumptions behind the downloadable Everside Health model - distilled from its pitch deck and publicly available information.
Product & value proposition
Everside operates onsite, nearsite, and virtual primary care health centers for employers. Employers pay a fixed, recurring, multi-year contract fee (replacing utilization-driven fee-for-service). Employees receive free or low-copay access to: primary care, mental health services, chronic condition management, wellness coaching, onsite labs/testing, occupational health, referral management, and pharmacy. A proprietary rules engine ingests medical & Rx claims, clinical & lab data, wellness & risk data, and social determinants to generate a 360-degree patient view and produce actions for patients and providers.
Key differentiators vs. industry:
- Same/next-day appointments vs. 56-day average wait
- 885 average patient panel size vs. 2,200 industry average
- NPS +85 vs. industry average -1.7
- 1.1% medical cost trend vs. 6–7% industry inflation
Market
- 100M+ Americans covered by self-funded plan sponsors in 2021
- Plan sponsor health benefit costs averaged 7.8% of total compensation in 2021
- Average annual family coverage premium (2021): $22,221 total ($16,253 plan sponsor + $5,969 worker)
- 87% of large employers believe health benefit costs will become unsustainable in the next 5–10 years
- Only 10% of plan sponsors currently use value-based care (VBC) solutions; 87% have shown interest
- 73% of plan sponsors plan to engage in VBC programs within the next 5 years (McKinsey survey)
Revenue model
- Fixed, recurring, multi-year contracts with employer plan sponsors
- Fee structure: Per-employee-per-month (PEPM) or per-health-center contract - specific pricing not disclosed in deck
- Channels: Direct B2B sales to self-funded employers (350+ clients as of deck date)
- Delivery models: Onsite health centers (employer-dedicated), nearsite health centers (shared/multi-employer), and virtual care
- Ancillary: Pharmacy, labs/testing embedded in health centers
Traction & metrics
All figures as of deck date (circa mid-2022 based on context):
- 575K+ patients
- 350+ employer clients
- 375+ health centers
- 400+ employed providers
- 34 U.S. states / 140+ markets
- 1,400+ employees
- NPS +85 (as of July 2022)
- 81% of patients report health improved after using services
- 75% of patients viewed their employer more favorably due to Everside access
- Clinical quality and outcomes metrics at 90th percentile or higher
- 30%+ cost savings for employers
- Best in KLAS: Employer Sponsored Healthcare Services 2022
Unit economics
- Medical cost trend for employers: 1.1% vs. 6–7% industry average
- Employer cost savings: 30%+
- Patient panel size: 885 per provider vs. 2,200 industry average
Competition / moat
Moat framing from deck:
- Lower panel sizes enable high-touch, relationship-based care (vs. volume-driven FFS model)
- Proprietary technology rules engine aggregating multi-source patient data (claims, clinical, labs, wellness, social determinants)
- Fixed-contract model aligns incentives with employers to reduce total cost of care (vs. FFS which rewards utilization)
- NPS +85 creates strong patient/employer retention
- Scaled national footprint (375+ health centers, 34 states) is a hard-to-replicate physical asset base
- Named competitors: Not explicitly named in deck
Team & funding ask / use of funds
Team:
- Chris Miller, CEO - prior: Trumpet Behavioral Health, DaVita
- Heather Dixon, CFO - prior: Walgreens Boots Alliance, Aetna
- Adam Johnson, Chief Growth & Strategy Officer - prior: Compass, Alight
- Tobias Barker MD, Chief Medical Officer - prior: Mass General Brigham, CVS Health
- Courtney Harwood, CMO - prior: CLEAR, Xerox
- Sampath Narayanan, CIO - prior: Concerto Health, Cognizant
- Allison Velez, Chief People Officer - prior: Optum, DaVita
- Michi Tsuda JD MBA, General Counsel - prior: Greenberg Traurig, Squire Patton Boggs
- Mason Reiner, SVP Innovation & Value Based Care - prior: R Health
Recommended financial model
- Archetype + why: Employer-sponsored healthcare services revenue model - B2B contracted recurring revenue with a per-health-center / PEPM structure. Closest archetype is a contracted services / recurring revenue 3-statement model with client cohort tracking. Not a pure SaaS ARR model (physical health centers are the delivery unit and carry significant capex/opex), not a pure insurance GWP/loss-ratio model (Everside is not the risk-bearer - the employer is). The correct frame is a health center P&L + employer contract revenue model: revenue is contract fees per client (or per enrolled life), costs are driven by health center count × cost per center and provider headcount × fully loaded cost per provider.
- Forecast horizon & granularity: 5-year annual model (2022–2027) with monthly build for Year 1; given physical build-out cycle, annual granularity is appropriate for Years 2–5.
- Key drivers & assumptions:
| Driver | Seed value |
|---|---|
| Employer clients (starting) | 350+ |
| Net new clients per year | ~50–75 |
| Health centers (starting) | 375+ |
| Health centers per client (avg) | ~1.1 |
| Patients per health center | ~1,533 (575K ÷ 375) |
| Total enrolled lives (starting) | 575,000+ |
| Enrolled lives growth (YoY) | ~15–20% |
| Providers employed (starting) | 400+ |
| Patient panel per provider | 885 |
| Employee count (starting) | 1,400+ |
| Employees per health center | ~3.7 (1,400 ÷ 375) |
| Provider cost (fully loaded) | ~$250–$300K/yr per employed provider |
| Non-provider opex per health center | ~$300–$400K/yr (rent, admin, supplies) |
| Gross margin | 20–35% (employer-sponsored primary care benchmarks); target improving over time |
| Employer medical cost savings delivered | 30%+ |
| Client churn | <5%/yr; long-term contracts, high switching cost |
| Contract length | 3–5 years; multi-year stated |
- Scenarios (Base / Bull / Bear - which variables flex):
- Base: 350 clients → 600 by Year 5; PEPM $100; gross margin 25%
- Bull: Accelerated employer adoption (73% VBC intent in 5 years); PEPM $120; gross margin 30%; health center utilization improves
- Bear: Employer budget pressure slows new wins; churn rises to 8%; PEPM held flat; new health center openings halved
- Required sheets / outputs:
- Assumptions - all drivers listed above with scenario toggle
- Client & Lives Build - cohort-based: new clients × avg lives per client → total enrolled lives per year
- Revenue - enrolled lives × PEPM × 12; break out onsite vs. nearsite vs. virtual if data becomes available
- Health Center P&L - revenue per center, direct costs (providers, facility), contribution margin per center
- Headcount & Opex - providers (panel-size-driven), non-clinical staff (center-count-driven), G&A, sales & marketing
- Income Statement - revenue, COGS (provider + center costs), gross profit, opex, EBITDA
- Balance Sheet - capex for health center build-out, working capital, debt (if applicable)
- Cash Flow Statement - operating CF, capex (growth investment in new centers), free cash flow
- KPI Dashboard - clients, enrolled lives, health centers, PEPM, revenue/center, gross margin %, EBITDA margin %
Frequently asked
Is the Everside Health financial model free?+
Yes. The Everside Health model is a free Excel (.xlsx) download with live formulas. Sign up with your email and the workbook is yours to keep, review, and edit.
What's included in the model?+
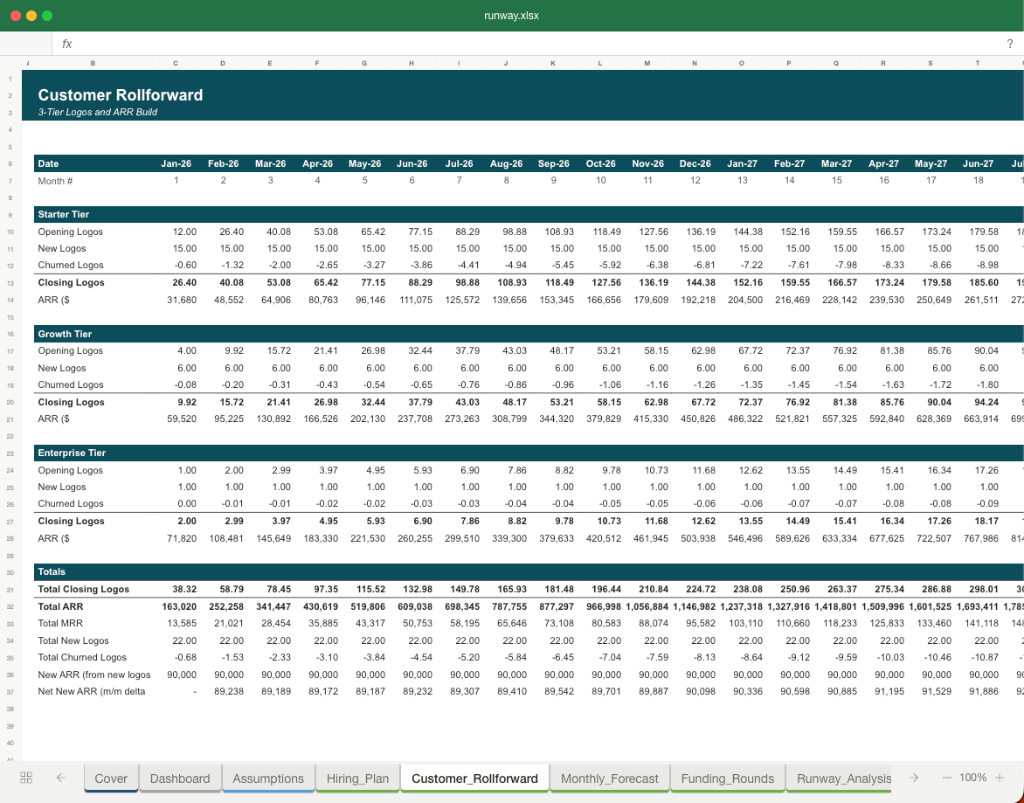
A 5-year monthly forecast with P&L, cash flow and runway, valuation (exit multiple plus a DCF cross-check), MOIC/IRR returns, and unit economics, with live formulas throughout.
How was this model built?+
It was built from Everside Health's pitch deck and publicly available information, then structured to investment-banking standards as a fully editable Excel model.
Can I change the assumptions?+
Yes. You can change assumptions and the live formulas will recalculate in the downloadable Excel model.
Have more financial modelling questions? Contact us

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Other Health-tech Startup Financial Models
Browse another startup in the same category.
98point6
B2B SaaS platform licensing an AI-powered virtual care technology stack to health systems, pivoted from running a direct-to-employer virtual clinic.
A-Champs
IoT-powered gamified training device (ROXs PRO) for sports/health professionals, evolving into a B2C smart coach app for families.

AccuRx
Patient-centred communication platform connecting everyone involved in a patient's care, starting with near-universal penetration in UK GP practices.

Aeris
Swiss-made premium air purifiers sold through DTC, retail, and dealer channels, with a recurring filter consumable attached to a connected mobile app.

Akido Labs
Akido Labs is a data-driven prevention platform that integrates siloed healthcare, municipal, and non-profit data to enable proactive outreach and case management for vulnerable populations (homeless, chronically ill, etc.).

Alloy
Telehealth + DTC subscription platform delivering menopause hormonal treatment (MHT) and holistic care to U.S. women 40+.

Astek Diagnostics
Point-of-care diagnostic device (Jiddu system) that confirms bacterial infections and antibiotic sensitivity in ~1 hour across four body fluid types (urine, CSF, effluent, blood).

Atom Limbs
Atom Limbs is building the first AI-powered, neural-controlled prosthetic arm sold direct-to-consumer on a subscription model.