Hazel Health Financial Model
Health-tech Startup Financials (Free Excel Download)
School-based telehealth platform delivering primary and urgent care to K-12 students via iPads at school and browsers at home.



professionals from Deloitte
Used by professionals from






About this model
Hazel Health delivers school-based telehealth primary and urgent care through iPads at school and browsers at home. The service gives students access to care in the settings where districts, families, and health plans can coordinate support.
School districts provide the B2B entry point, while health-plan reimbursement supports visit economics. Growth therefore depends on district contracts, covered-student populations, school activation, clinical availability, and utilisation rather than conventional software-seat adoption.
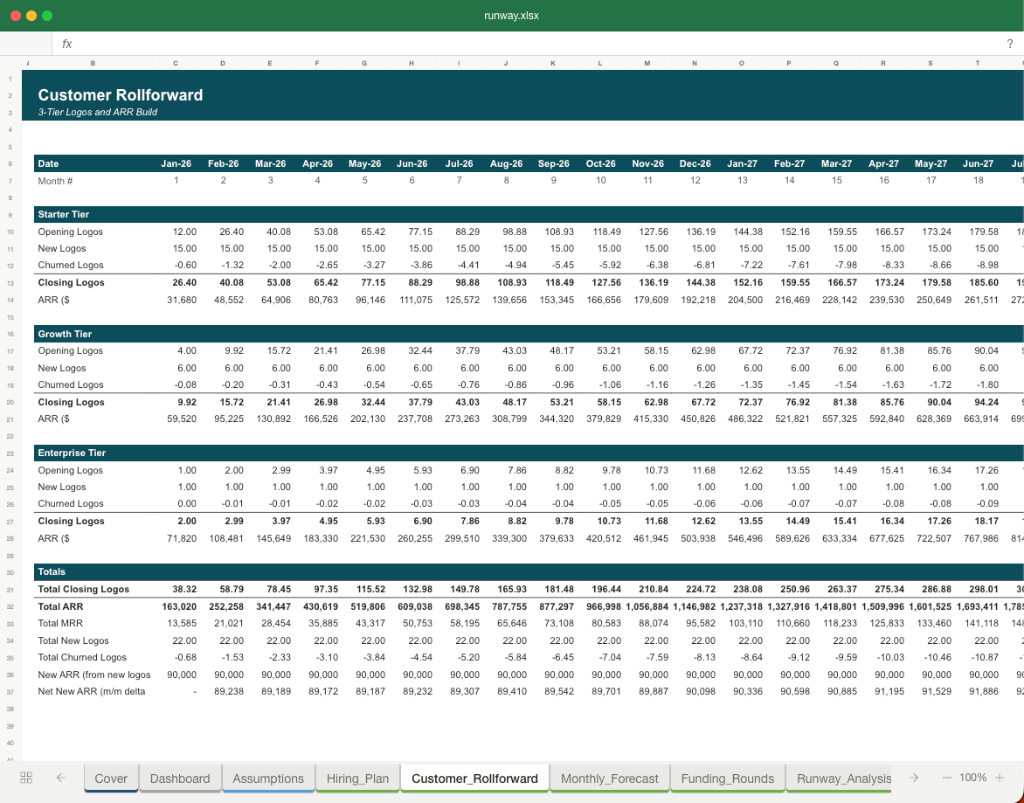
The model forecasts district contracts, covered students, utilisation, reimbursement per visit, clinician capacity, and renewal. It includes school onboarding, care-team labour, technology and support costs, payer collections, market-launch expenses, gross margin, operating cash flow, and runway.
A turnkey financial model
Live formulas, no hardcoded values
Outputs are driven by live formulas, so the workbook updates from its assumptions instead of relying on hardcoded results.
All assumptions in one tab
Inputs are clearly marked in the Assumptions tab and separated from calculations, making it clear what to change and what to leave intact.
Statements always balancing
For integrated-statement models, the balance sheet, cash flow, and supporting schedules tie through properly.
Distinct schedules for clarity
Debt, working capital, taxes, and cash flow can get messy quickly. We group calculations in clear schedules, not across disconnected tabs.
No hidden macros or external links
There are no unexplained external workbook links or macros to undermine auditability or portability.
Changes flow through the model
Update a key driver and see the impact carry through the forecast, financing, and return outputs. We never use hardcoded numbers in formulas.
About Hazel Health
hazel.co
How to build a detailed financial model for Hazel Health
A complete walkthrough of the business, drivers, and assumptions behind the downloadable Hazel Health model - distilled from its pitch deck and publicly available information.
Product & value proposition
- Hazel at School (core): Telehealth visits via iPad during the school day. Licensed MDs, NPs, PAs trained in school-based care. Addresses 90% of primary/urgent care needs.
- Hazel at Home (extension): Same providers, web-browser access before/after school, weekends, holidays, summers.
- Hazel for Families (future): Broader family coverage - not yet launched.
- Value props: 9-in-10 program enrollment rate; 90% same-day return-to-class; 3-minute wait time; multilingual / all demographics.
Market
- TAM: ~$100B total addressable annual spend, composed of:
- $150B total K-12 healthcare spend
- $90B ambulatory pediatric cost (wellness & diagnosis visits)
- $10B unnecessary ER costs for children
- (Source cited: JAMA Pediatrics, NCES annual reports)
- SAM: 30M students with limited or no access - segmented as 5M (SBHC closed/no telehealth) + 10M (no established care) + 15M (health desert) = 30M subtotal.
- SOM: 2M students - stated 2020 growth target. Existing coverage 13M students in current states; new states add 17M.
Revenue model
- Primary channel: School district contracts (B2B - districts are the entry point and trusted relationship).
- Reimbursement: Health plans cover visits; deck notes expanded coverage and shift toward reimbursement parity post-COVID.
- Unit of sale: Likely per-student enrolled per district, or per-visit reimbursement from payer - not specified.
- Hazel at Home and Hazel for Families represent upsell / extension revenue streams off the school district relationship.
Traction & metrics
- Program enrollment rate: 9 in 10 students enroll
- Return-to-class same day: 90%
- Chronic absenteeism reduction: 25% year-over-year
- Patient experience rating: 4.9/5.0 by schools
- Wait time: 3 minutes
- Telehealth utilization: 70%+ (vs. 10% national benchmark, 15% parents who have used for child, 64% interested)
- Geographic footprint: 7 states at time of deck
- Students accessible: Existing states cover 13M students; targets 17M new students
Competition / moat
- Competitive position: Claims market leadership in school-based telehealth.
- Differentiation: School as trusted entry point drives 70%+ utilization vs. 10% industry benchmark; clinically trained providers; multilingual/all-demographics focus; same-day return-to-class protocol.
- Regulatory moat: Cross-state licensure barriers easing (noted as tailwind, not moat).
Team & funding ask / use of funds
- Josh Golomb (CEO): Co-founder DaVita Rx (scaled $50M → $1B+ revenue); CEO Paladina Health. Stanford undergrad + MBA.
- Nick Woods (CTO): Co-founder; 25+ years product/engineering; former Apple senior software engineer. Santa Clara University.
- Rob Darzynkiewicz (CMO): Board-certified Emergency Medicine, 13+ years, Pediatric Emergency Director. NY Medical College.
- Raquel Antunez (VP Education Markets): 20+ years education sector; former school principal. USC-Sacramento MA.
- Jeannie Chen (VP Clinical Operations): Former Chief Strategy & People Officer at InnerChange; DaVita. Duke + Wharton MBA.
- Matt Weissert (VP Operations): 20+ years healthcare ops; Paladina Health; DaVita Division VP; US Air Force. USAFA + UWF MBA.
- Funding ask: Mentioned ("with additional capital, we will reach nearly 30 million school-age children") but dollar amount not stated.
- Use of funds: Geographic expansion to new states / student coverage.
Recommended financial model
Archetype + why: B2B healthcare services revenue model with per-student (capitated or per-visit) economics. Most appropriate structure is a district-contract / covered-lives revenue model - similar to a capitated managed care or per-member-per-month (PMPM) model, layered with fee-for-service reimbursement from health plans. This is an operating forecast model, not an M&A or SPAC deck.
Forecast horizon & granularity:
- 5 years (Year 1–5), annual columns; Year 1 broken into quarters for cash planning.
- Monthly granularity not warranted given the B2B contract cadence.
Key drivers & assumptions:
*Student coverage (top of funnel)*
- Students covered at period start: 13M existing states; 2M active target for near term
- New students added per year (district wins × avg district size): Model as new district wins; avg K-12 district size ~3,000–5,000 students
- States in market: 7 currently; 15–20 target
*Enrollment & utilization*
- Enrollment rate: 90% (9-in-10)
- Visit utilization per enrolled student per year: ~1.5–2.5 visits/year; benchmark from school-based health center data
- Visit volume = covered students × enrollment rate × visits per student per year
*Revenue*
- Revenue per visit (blended reimbursement): ~$50–$100/visit based on pediatric telehealth reimbursement norms; exact rate not in deck
- Alternatively, if modeled as PMPM contract: ~$5–$15 PMPM per covered student; not confirmed in deck
- Hazel at Home / upsell revenue: small % uplift on core; model as % of district contract value
*Cost structure*
- Clinical provider cost (MDs/NPs/PAs): largest variable cost; model as cost per visit or FTE-per-student ratio
- Technology / platform: semi-fixed; scale with student count
- District sales & onboarding (CAC proxy): sales cycle 6–12 months; model as sales headcount + onboarding cost per new district
- G&A: scale with headcount
*Growth*
- New district wins per year: aggressive ramp; calibrate to reach 2M students in near term
- Churn: low (B2B contract; public school district stickiness); model 5–10% district churn
- Reimbursement parity uplift: modest rate increase as payer coverage expands [supported by slide 11]
Scenarios (Base / Bull / Bear - which variables flex):
- Bear: Slower district wins, payer reimbursement below parity, higher clinical staffing cost
- Base: 2M students in near term per stated target; steady district win rate; reimbursement at mid-range
- Bull: Rapid payer parity + cross-state licensure expansion, Hazel at Home contributing material revenue, faster state rollout
Required sheets / outputs:
- Assumptions - all drivers in one place
- District pipeline - new districts × avg students, by state/cohort
- Student coverage & visit volume bridge
- Revenue build (visit-based or PMPM, plus Hazel at Home)
- P&L - revenue, clinical costs, technology, S&M, G&A, EBITDA
- Headcount plan (clinical FTEs scale with visit volume; sales/ops scale with district count)
- Cash flow & funding need (to show capital required for the expansion stated in deck)
- KPI dashboard - students covered, enrollment rate, utilization rate, revenue per student, gross margin
Frequently asked
Is the Hazel Health financial model free?+
Yes. The Hazel Health model is a free Excel (.xlsx) download with live formulas. Sign up with your email and the workbook is yours to keep, review, and edit.
What's included in the model?+
A 5-year monthly forecast with P&L, cash flow and runway, valuation (exit multiple plus a DCF cross-check), MOIC/IRR returns, and unit economics, with live formulas throughout.
How was this model built?+
It was built from Hazel Health's pitch deck and publicly available information, then structured to investment-banking standards as a fully editable Excel model.
Can I change the assumptions?+
Yes. You can change assumptions and the live formulas will recalculate in the downloadable Excel model.
Have more financial modelling questions? Contact us

Created by ex-finance professionals
Hey, I’m Alex and I created Finamodel.
Over my years in the finance industry I kept building the same models over and over again. Same structure, same assumptions, different logo. So I started building frameworks to turn them into clean, reusable templates.
Every model here is one I’d actually use for a client, and I personally vet each one before it goes up.
I’m not an expert in every industry, but I’ve built enough models to know what belongs in one. And when something is completely foreign to me, I reach out to my network for experts to work on our models with us.
Having a template library on hand cuts a first build from hours to minutes.
Need help finding your model? You’ll find me in the Finamodel app!
Other Health-tech Startup Financial Models
Browse another startup in the same category.
98point6
B2B SaaS platform licensing an AI-powered virtual care technology stack to health systems, pivoted from running a direct-to-employer virtual clinic.
A-Champs
IoT-powered gamified training device (ROXs PRO) for sports/health professionals, evolving into a B2C smart coach app for families.

AccuRx
Patient-centred communication platform connecting everyone involved in a patient's care, starting with near-universal penetration in UK GP practices.

Aeris
Swiss-made premium air purifiers sold through DTC, retail, and dealer channels, with a recurring filter consumable attached to a connected mobile app.

Akido Labs
Akido Labs is a data-driven prevention platform that integrates siloed healthcare, municipal, and non-profit data to enable proactive outreach and case management for vulnerable populations (homeless, chronically ill, etc.).

Alloy
Telehealth + DTC subscription platform delivering menopause hormonal treatment (MHT) and holistic care to U.S. women 40+.

Astek Diagnostics
Point-of-care diagnostic device (Jiddu system) that confirms bacterial infections and antibiotic sensitivity in ~1 hour across four body fluid types (urine, CSF, effluent, blood).

Atom Limbs
Atom Limbs is building the first AI-powered, neural-controlled prosthetic arm sold direct-to-consumer on a subscription model.